- meta-analysis
- 9 min read
- By George Burchell
- View publications on PubMed
- ORCID
Meta-Analysis Guide: Steps, Heterogeneity and Forest Plots
A meta-analysis is the statistical combination of results from two or more separate studies: one summary estimate and a confidence interval. Pool only when the participants, interventions, comparisons, and outcomes are similar enough for that average to answer a clinically meaningful question (MECIR C62; Cochrane Handbook, section 10.10.1). If they are not, keep the review and do not pool. The steps below follow Handbook chapter 10 (version 6.5.1, last updated November 2026).
Steps
The diamond comes last. Settle the question, eligibility, selection, data collection, risk of bias, and the comparisons first (section 10.1).
-
Protocol. Name the comparisons, the effect measure, the model, and the heterogeneity investigations before you see the results (section 10.10.1; section 10.11). Draft the wording in the protocol guide. It does not register the protocol.
-
Compatible effects. Summarise every study on one scale, then take a weighted average. More precise studies count for more (section 10.2.1). Inverse-variance pooling needs an effect and its standard error (section 10.3.1). Reverse a backwards scale and say so (MECIR C61).
-
Model. A fixed-effect model assumes one common effect. A random-effects model assumes different but related effects (section 10.10.4.1). Do not choose the model from a heterogeneity test.
-
Heterogeneity. When you pool, assess the variation (MECIR C63). Read I², τ², and Q with the forest plot. A large I² is not a rule to stop or to continue.
-
Report. PRISMA 2020 items 13 and 20 cover the methods and the results (Page et al., BMJ 2021). The PRISMA checklist records where each item sits. Using it is aligned with PRISMA 2020. It does not certify the review.
Before you pool
- One question a reader could act on (MECIR C62).
- One effect measure, or a justified conversion, with the direction stated (MECIR C61).
- Cluster, crossover, and multi-arm data handled so people are not counted twice (MECIR C66 and C70).
- Heterogeneity analyses you will trust, written in the protocol (MECIR C68).
- Model and software named (PRISMA 2020 item 13d).
Reading a forest plot
SystematicReviewTools.app does not pool effects or draw forest plots. The figure is synthetic: studies A–D were invented, then pooled so the diamond matches the squares. Not a clinical result.
An odds ratio below 1 favours the fictional intervention. The vertical line is 1. Square area is the random-effects weight. The horizontal line is the 95% confidence interval. The diamond is the pooled estimate and its interval (section 10.2.1). The dashed bar is an illustrative 95% prediction interval.
| Study | Odds ratio | 95% CI | Random-effects weight |
|---|---|---|---|
| Study A (synthetic) | 0.62 | 0.41 to 0.94 | 28.2% |
| Study B (synthetic) | 0.80 | 0.55 to 1.16 | 31.8% |
| Study C (synthetic) | 1.05 | 0.70 to 1.58 | 28.8% |
| Study D (synthetic) | 0.48 | 0.22 to 1.05 | 11.2% |
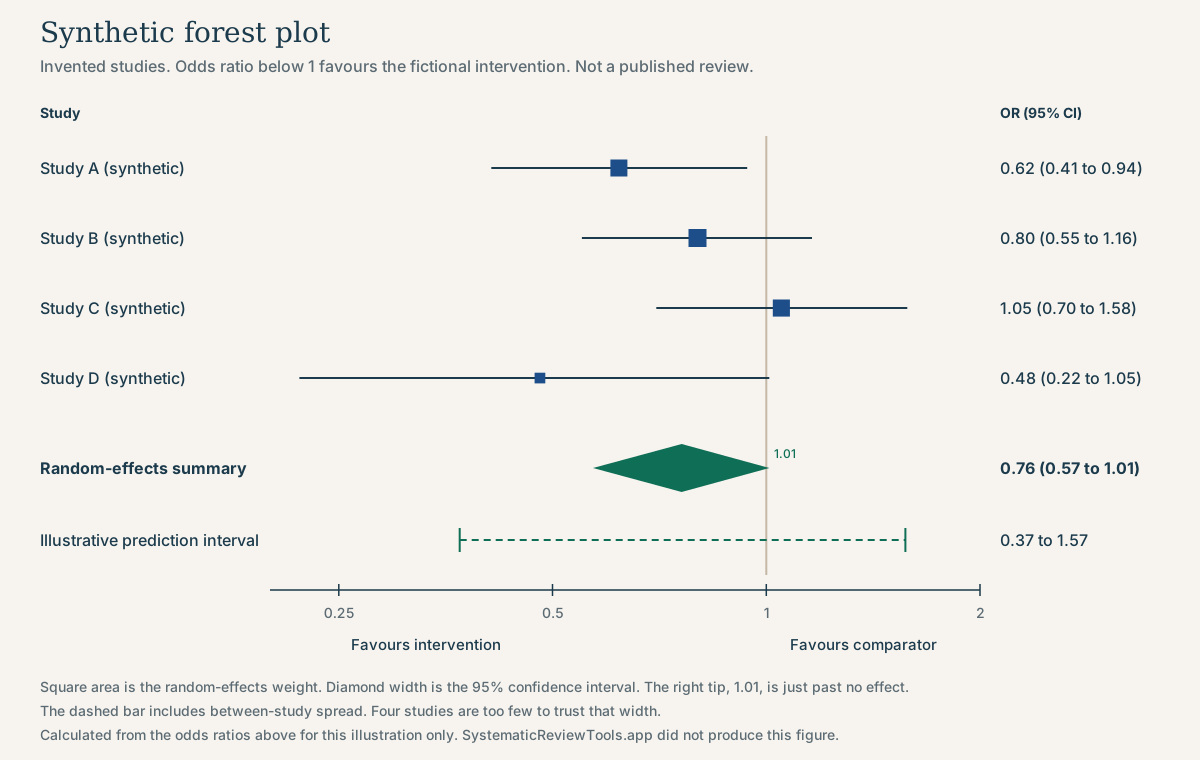
Study A lies wholly below 1. Study C sits above 1. B and D cross the line. Study D is the smallest square because weight follows precision (section 10.2.1).
The random-effects summary is 0.76 (95% CI 0.57 to 1.01). A fixed-effect pool is 0.77 (95% CI 0.62 to 0.96). Do not prefer an interval only because it excludes 1 (section 10.10.4.1). Q is 4.72 on 3 degrees of freedom (P = 0.19), I² is 36%, and τ² is 0.031. A non-significant Q test with few studies does not prove the effects match (section 10.10.2).
The dashed bar, about 0.37 to 1.57, uses the Handbook t with k−1 degrees of freedom (Riley et al. use k−2). It shows spread, not the precision of the mean, and it includes benefit and harm (section 10.10.4.3; Riley et al., BMJ 2011). Four studies are too few to trust it. The Handbook's example is five or more, without clear funnel-plot asymmetry. The pool is inverse-variance on the log odds ratio, τ² is the DerSimonian–Laird estimate (section 10.10.4), and I² is 100% × (Q − degrees of freedom) / Q (Higgins et al., BMJ 2003).
Heterogeneity
Variability among studies is heterogeneity. Section 10.10.1 separates clinical diversity (participants, interventions, outcomes), methodological diversity (design, measurement, risk of bias), and statistical heterogeneity (effects differ by more than chance). Clinical diversity does not forbid a pool: a class-level question can average across drugs in that class (MECIR C62).
Q tests whether differences fit chance alone. A low P value is evidence of heterogeneity, but with few or small studies a non-significant result is not homogeneity. Some reviewers use 0.10 rather than 0.05. Many large studies can flag trivial differences (section 10.10.2).
I² is the percentage of variability due to heterogeneity rather than chance (Higgins et al., BMJ 2003), not the size of the differences. Rücker and colleagues showed that raising precision, with the same underlying effects, leaves τ² about the same while I² climbs toward 100% (Rücker et al., 2008). τ² measures the spread; judge it against clinical relevance.
Higgins et al. tentatively called 25%, 50%, and 75% low, moderate, and high, and said a naive categorisation is not always appropriate. The Handbook uses overlapping bands (0–40%, 30–60%, 50–90%, 75–100%) and ties importance to size and direction. MECIR C63 says "use of simple thresholds to diagnose heterogeneity should be avoided." An I² above 50% or 75% is not an automatic stop or go.
τ² is the variance of the underlying effects. The summary confidence interval is uncertainty about the mean, not that spread (section 10.10.4.2). A prediction interval puts the spread on the effect's scale (section 10.10.4.3). In 479 statistically significant random-effects meta-analyses with I² above zero, from Cochrane intervention reviews in 2009–2013, 72.4% had a 95% prediction interval that still allowed a null or opposite effect (IntHout et al., BMJ Open 2016).
If effects disagree, check data entry before quoting an average (section 10.10.3). A review need not contain a meta-analysis. Pre-specify subgroups; label any post-hoc ones. Use a formal test (MECIR C67 and C68). Do not drop a study only for its result (MECIR C71). A difference by setting, dose, or population is effect modification (section 10.11.1). Report planned investigations, including null ones (PRISMA 2020 item 20c).
When to pool and when not to
| Situation | Decision | Source |
|---|---|---|
| Same question and a shared effect measure | Pooling can be meaningful | MECIR C62 |
| Different drugs or populations, one class-level question | Pooling can fit if you define the average | Handbook 10.10.1 |
| Effects disagree in direction | Do not quote an average | Handbook 10.10.3 |
| No estimate and no inputs to calculate one | Leave that study out | Handbook 10.3.1 |
| Different outcomes, or scales that point opposite ways | Do not combine them | MECIR C61, C62 |
| Cluster, crossover, or multi-arm data not adjusted | Do not pool them naively | MECIR C66, C70 |
| I² high or I² low | Not an automatic stop or go | MECIR C63; Rücker 2008; Higgins 2003 |
Fixed-effect and random-effects models
A fixed-effect analysis assumes one underlying effect, also called a common-effect or equal-effects assumption (section 10.3.1). The summary is a typical effect from the included studies. Its confidence interval usually ignores remaining heterogeneity (section 10.10.4.1; MECIR C69).
A random-effects analysis assumes effects follow a distribution, usually normal. The summary is that mean. With heterogeneity the interval is wider and smaller studies get more weight, so bias in small studies pulls the mean (section 10.10.4). The methods agree when heterogeneity is absent. The Handbook recommends neither model for every review.
Funnel plots address missing results, not heterogeneity. MECIR C73 says to consider non-reporting bias (Handbook section 13.4).
What to report
PRISMA 2020 items 13a–13f and 20a–20d cover the model, heterogeneity methods, software, and every synthesis, exploration, and sensitivity analysis (Page et al., BMJ 2021). Say which group an effect favours. Record items on the PRISMA checklist and draft paragraphs in the manuscript outline. This site does not run the analysis. That record is aligned with PRISMA 2020 and with Cochrane guidance. Acceptance is the journal's decision.
Before you submit, the manuscript should contain:
- The model, heterogeneity methods, and software (item 13d).
- The summary, its interval, heterogeneity measures, and the direction of effect (item 20b).
- Every planned exploration, including null ones (item 20c; MECIR C68).
- The sensitivity analyses (item 20d; MECIR C71).
- A prediction interval when a random-effects model has enough studies (section 10.10.4.3).
Frequently asked questions
What is a meta-analysis?
A meta-analysis is a weighted average of compatible effect estimates from two or more studies, with a confidence interval. Pool only when participants, interventions, comparisons, and outcomes are similar enough for a clinically meaningful answer.
When should results not be pooled?
Do not pool if the studies do not share one meaningful question, if effects disagree in direction, if the numbers for a common effect are missing, or if cluster, crossover, or multi-arm data would distort precision. A review can stop without a meta-analysis.
Does an I² above 50% or 75% mean the meta-analysis must stop?
No. I² is the share of variability due to heterogeneity rather than chance, and it can near 100% as studies get more precise even when τ² does not. MECIR C63 says not to diagnose heterogeneity with a simple threshold.
What does a prediction interval add?
A random-effects confidence interval locates the mean effect. A prediction interval shows the spread of underlying effects. The Handbook encourages one when there are enough studies, with five or more as the example, and no clear funnel-plot asymmetry.
Do subgroup analyses have to be specified in advance?
Specify investigations you will trust before seeing the results. Compare subgroups with a formal test. A significant effect in one subgroup only does not show that the subgroups differ.
Sources
Checked 5 November 2026.
- Deeks JJ, Higgins JPT, Altman DG, McKenzie JE, Veroniki AA, Simmonds M (editors). Chapter 10, updated November 2026. Cochrane Handbook version 6.5.1. Chapter 10.
- MECIR C61–C73, including mandatory C62 and C63. Standards.
- Higgins JPT, Thompson SG, Deeks JJ, Altman DG. BMJ. 2003;327:557. doi:10.1136/bmj.327.7414.557.
- Rücker G, Schwarzer G, Carpenter JR, Schumacher M. BMC Med Res Methodol. 2008;8:79. doi:10.1186/1471-2288-8-79.
- Riley RD, Higgins JPT, Deeks JJ. BMJ. 2011;342:d549. doi:10.1136/bmj.d549.
- IntHout J, Ioannidis JPA, Rovers MM, Goeman JJ. BMJ Open. 2016;6:e010247. doi:10.1136/bmjopen-2015-010247.
- Page MJ, McKenzie JE, Bossuyt PM, et al. BMJ. 2021;372:n71. doi:10.1136/bmj.n71.

About the Author
Connect on LinkedInGeorge Burchell
George Burchell is a specialist in systematic literature reviews and scientific evidence synthesis with significant expertise in integrating advanced AI technologies and automation tools into the research process. With over four years of consulting and practical experience, he has developed and led multiple projects focused on accelerating and refining the workflow for systematic reviews within medical and scientific research.